Summary
Thyroid disease in pregnancy (hypothyroidism or Graves’ hyperthyroidism) requires careful management; untreated disease increases risks of miscarriage, preeclampsia, growth restriction, and impaired neurodevelopment. Diagnosis rests on TSH and free T4 against trimester-specific ranges, as hormonal shifts affect lab values. Hypothyroidism is treated with levothyroxine, with the dose raised 20–30% at pregnancy confirmation. Hyperthyroidism is treated with antithyroid drugs—PTU in the first trimester, methimazole afterwards—aiming for free T4 at the upper limit of normal; radioactive iodine is contraindicated. Women with Graves disease need TSH receptor antibody testing and fetal surveillance, as antibodies cross the placenta. Thyroid storm is a rare life-threatening emergency treated with PTU, beta-blockers, iodine, and corticosteroids with close monitoring.
Overview
Thyroid disease is common in women of childbearing age and may significantly impact both maternal and fetal outcomes. Diagnosis during pregnancy is challenging, as typical symptoms—such as fatigue, heat intolerance, constipation, palpitations, and weight changes—often overlap with physiological changes of normal pregnancy.
Pregnancy alters thyroid physiology in three ways, making standard non-pregnant reference ranges for thyroid function tests (TFTs) inappropriate:
- Estrogen-induced TBG rise: estrogen boosts hepatic thyroxine-binding globulin (TBG) synthesis and slows its clearance → more hormone is protein-bound → the thyroid raises output until the free fraction normalizes → total T4 and T3 reach about 1.5× nonpregnant values while free T4 stays near normal.
- Plasma volume expansion: enlarges the pool that thyroid hormone must fill; overall hormone production rises by about 30–50%.
- Relative iodine deficiency: renal iodine clearance increases and the placenta and fetus take up iodine, so the recommended intake rises to 220 µg/day.
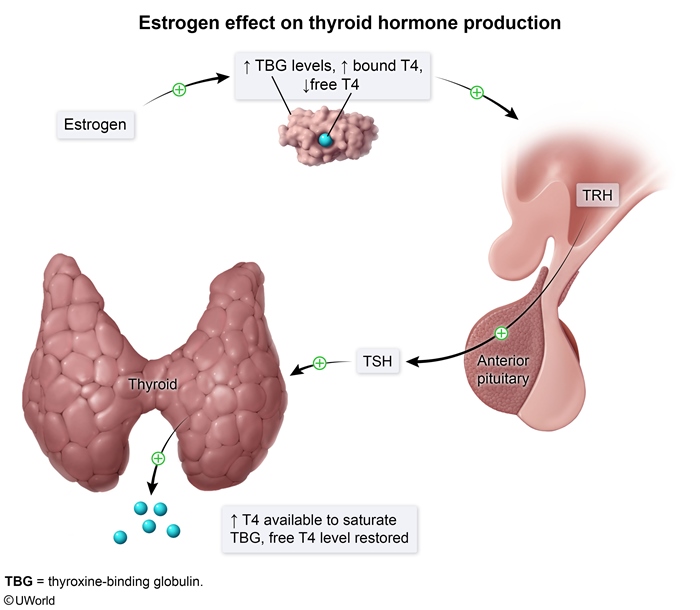
Any estrogen state (oral contraceptives, hormone therapy) shifts total hormone levels the same way — see the conditions that raise or lower TBG.
| فخ امتحاني | |
|
In pregnancy, high estrogen raises TBG, and consequently total T3 and T4 rise deceptively; therefore, we always rely on free T4 with trimester-specific TSH reference ranges. Remember that in the first trimester, hCG causes transient TSH suppression and physiologically increases free T4. |
تذكر |
Maternal and Fetal Thyroid Physiology in Pregnancy
hCG and maternal thyroid tests
- During early pregnancy, hCG — which shares its α-subunit with TSH — weakly stimulates the TSH receptor; around its peak at 10–12 weeks it transiently suppresses TSH and increases free T4 in the first trimester, followed by a gradual decline in free T4 as gestation advances.
- A low first-trimester TSH with a normal free T4 is usually physiologic, not hyperthyroidism.
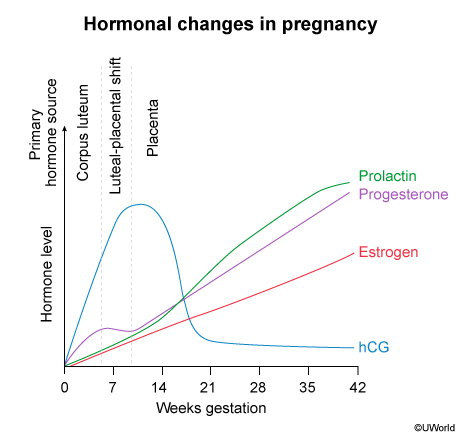
- Best initial test: TSH, interpreted with trimester-specific (or assay-specific) ranges; when no local range exists, a TSH above about 4.0 mU/L is taken as elevated.
- Measurement of free T4 is the most reliable indicator of thyroid function in pregnancy, as total T3 and T4 levels are elevated due to increased TBG; a total T4 is usable only when the nonpregnant upper limit is raised by 50% (from about 16 weeks).
The expected first-trimester pattern is set out in maternal thyroid test changes in the first trimester, and the test patterns of normal pregnancy, hyperthyroidism and hypothyroidism are compared side by side.
Fetal thyroid development
- Fetal thyroid development: the gland starts concentrating iodine and making T4 from about 10–12 weeks, with meaningful hormone output from about 12–14 weeks.
- The gland and its hypothalamic-pituitary-thyroid axis are not fully functional until about 18–20 weeks.
- During the first half of pregnancy — when neurogenesis begins — the fetal brain therefore depends almost entirely on maternal T4.
Placental transfer
What crosses the placenta explains the fetal risks of each maternal disorder and its treatment:
| Placental transfer in maternal thyroid disease: Substance → what crosses → why it matters | |
| Crosses freely | Substance | Clinical significance in pregnancy |
| Iodine | Fetal hormone synthesis depends on maternal intake; deficiency → fetal hypothyroidism and goiter; excess iodide (e.g., iodide-containing drugs) → neonatal goiter/hypothyroidism |
| TRAb (IgG) | Stimulating antibodies → fetal/neonatal thyrotoxicosis (tachycardia, goiter, growth restriction, hydrops); blocking antibodies → transient neonatal hypothyroidism |
| Antithyroid drugs (PTU, methimazole) | Suppress the fetal thyroid → fetal hypothyroidism and goiter if the mother is overtreated |
| Limited transfer | Substance | Clinical significance in pregnancy |
| Maternal T4 | Only source of thyroid hormone for the fetal brain in the first trimester; maternal hypothyroidism → impaired neurocognitive development |
| Does not cross | Substance | Clinical significance in pregnancy |
| TSH | Maternal TSH never reaches the fetus; fetal TSH reflects only the fetal axis |
| ملاحظة سريرية | |
|
The fetal thyroid begins to accumulate iodine and synthesize T4 at approximately 10–12 weeks, but its output remains limited until 18–20 weeks; during the first half of pregnancy the fetus depends on limited placental transfer of maternal T4 for neurodevelopment, whereas TSH does not cross the placenta. |
ملاحظة |
Hypothyroidism in Pregnancy
Frequency and causes
- Frequency: overt hypothyroidism complicates fewer than 1 in 100 pregnancies; subclinical hypothyroidism (↑ TSH, normal free T4) is several times more common.
- Globally, iodine deficiency is the most common cause, while Hashimoto’s thyroiditis (anti-TPO antibodies) predominates in developed, iodine-sufficient regions.
- Other causes: prior thyroidectomy or radioiodine ablation; rarely pituitary disease (TSH low or inappropriately normal).
Diagnosis
- Overt: TSH above the trimester-specific limit with a low free T4. Subclinical: high TSH with a normal free T4.
- Symptoms (fatigue, constipation, cold intolerance, weight gain) are nonspecific, and many women are asymptomatic.
Complications of untreated disease
- Miscarriage
- Preeclampsia and gestational hypertension
- Placental abruption
- Intrauterine growth restriction (IUGR)
- Stillbirth
- Impaired neurocognitive outcomes in offspring — the key fetal risk, greatest when the first half of pregnancy is undertreated.
- Also preterm delivery, cesarean delivery and postpartum hemorrhage.
| Untreated maternal hypothyroidism: "Low T4 MAPS IN the harm" | |
|
جملة تذكرية |
Management
- Step 1 – Before conception: optimize levothyroxine so TSH sits in the low-normal range; do not raise the dose pre-emptively.
- Step 2 – Known hypothyroidism, pregnancy confirmed: increase levothyroxine by about 20–30% at the positive test (e.g., two extra daily doses per week); total requirements rise by 30–50% during pregnancy.
- Step 3 – New overt hypothyroidism in pregnancy: start levothyroxine immediately — it is safe and the treatment of choice; never defer treatment to the postpartum period.
- Step 4 – Monitor: TSH every 4 weeks until stable through mid-gestation, then at least once per trimester. The therapeutic goal is maternal biochemical euthyroidism, with TSH maintained in the lower half of the trimester-specific range.
- Step 5 – After delivery: return to the pre-pregnancy dose and recheck TSH about 6 weeks postpartum.
- Subclinical hypothyroidism: treatment is individualized and favored when anti-TPO antibodies are present.
- The hypothyroidism in pregnancy management summary collects these steps.
- Neonatal goiter: neonatal thyroid dysfunction may also occur, with maternal iodine exposure (e.g., iodide-containing medications) being a recognized cause of neonatal goiter — excess iodide switches off the fetal thyroid (Wolff–Chaikoff effect).
| فخ امتحاني | |
|
A woman with hypothyroidism, once pregnancy is confirmed, requires an increase in levothyroxine dose (total requirements increase by 30–50% during pregnancy); be aware that maternal exposure to iodide-containing medications can cause neonatal goiter. |
تذكر |
Hyperthyroidism in Pregnancy
Causes
- Hyperthyroidism occurs in <1% of pregnancies, with Graves’ disease (GD) accounting for ~95% of cases that need treatment.
- hCG-mediated thyrotoxicosis: gestational transient thyrotoxicosis with hyperemesis gravidarum or multiple gestation; very high hCG in gestational trophoblastic disease (molar pregnancy) can cause overt hyperthyroidism. Biochemically more frequent than Graves disease but self-limited, usually settling by the early second trimester.
- Toxic nodular disease: toxic adenoma or toxic multinodular goiter (palpable nodules).
- Thyroiditis: release of preformed hormone from damaged follicles; the hyperthyroid phase is transient and needs no antithyroid drug.
Clinical features
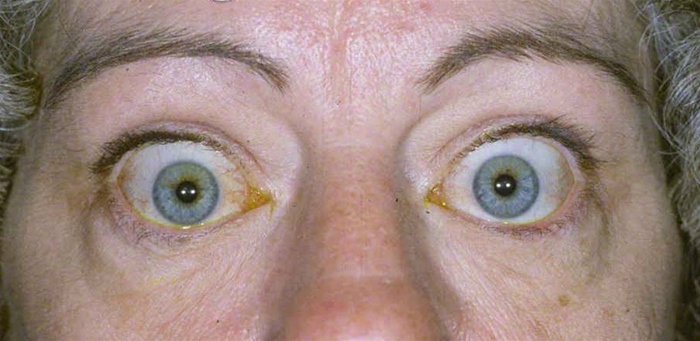
Clinical features distinguishing hyperthyroidism from normal pregnancy include tremor, weight loss (or poor weight gain despite good intake), ophthalmopathy, and pretibial myxedema; a diffuse goiter and resting tachycardia support the diagnosis. Proptosis and pretibial myxedema are specific to Graves disease.
Diagnosis
- Serum (first-line): suppressed TSH with free T4 (± T3) above the trimester-specific range = overt hyperthyroidism. Total T3/T4 are high in every pregnancy and cannot be used unadjusted.
- TRAb: positive in Graves disease, negative in gestational transient thyrotoxicosis. Measure it in every woman with current or past Graves disease — even after thyroidectomy or radioiodine — and, if raised, repeat at about 18–22 weeks to judge fetal risk.
- Imaging: thyroid ultrasound is the imaging modality of choice; radioactive iodine scans are contraindicated.
- Fetal surveillance: TRAb-positive women should undergo serial ultrasound surveillance for fetal thyrotoxicosis (fetal tachycardia, goiter, growth restriction, hydrops).
| Gestational transient thyrotoxicosis vs Graves disease | |
|
A first-trimester woman with hyperemesis, low TSH and mildly high free T4 but no goiter, no eye signs and negative TRAb has hCG-mediated (gestational transient) thyrotoxicosis: give supportive care only — no antithyroid drugs; it settles by the mid-second trimester. Positive TRAb, goiter or ophthalmopathy point to Graves disease, which needs treatment. |
تذكر |
Management
- Step 1 – Decide who needs drugs: overt Graves or nodular hyperthyroidism → treat. Gestational transient thyrotoxicosis and subclinical hyperthyroidism → supportive care (antiemetics, fluids) and monitoring.
- Step 2 – First-line: antithyroid drugs (ATDs): propylthiouracil (PTU) during the first trimester due to lower teratogenicity, and methimazole/carbimazole thereafter due to hepatotoxicity risk with prolonged PTU use. Methimazole embryopathy includes aplasia cutis, choanal and esophageal atresia.
- Step 3 – Target: maintain maternal free T4 in the upper normal range, using the lowest effective dose to minimize fetal hypothyroidism or goiter (ATDs cross the placenta).
- Step 4 – Symptom control: beta-blockers (propranolol or metoprolol) short-term only; prolonged use is linked to growth restriction and neonatal bradycardia or hypoglycemia.
- Step 5 – Monitor: TSH and free T4 about every 4 weeks (range 2–6 weeks); TSH may stay suppressed for weeks after control.
- Step 6 – Surgery: thyroidectomy only in the second trimester, for the indications in the table below; radioactive iodine is contraindicated — it ablates the fetal thyroid once the gland starts trapping iodine.
- Step 7 – Postpartum: Graves disease often flares after delivery; ATD doses usually need readjustment to prevent relapse.
| Antithyroid drug by trimester: the "P-M" rule | |
|
جملة تذكرية |
| Treatment options for hyperthyroidism in pregnancy | ||||
|---|---|---|---|---|
| Feature | Propylthiouracil (PTU) | Methimazole / carbimazole | Radioactive iodine | Thyroidectomy |
| When | 1st trimester (organogenesis) | 2nd and 3rd trimesters | Never in pregnancy | 2nd trimester, only if needed |
| Why | Lower teratogenic risk than methimazole | Less liver toxicity than prolonged PTU | Would ablate the fetal thyroid once it traps iodine (from about 10–12 weeks) | Definitive control when drugs fail or cannot be used |
| Main risk | Hepatotoxicity (rare acute liver failure) | Embryopathy when given in the 1st trimester | Congenital (fetal) hypothyroidism | Surgical and anesthetic risk; hypoparathyroidism, nerve injury |
| Practical notes | Lowest effective dose, e.g., 50–100 mg orally every 8 hours; also blocks T4 → T3 conversion | Lowest effective dose, once daily | Contraindicated (radioiodine scans too) | Severe ATD reaction, very high dose needs, persistent nonadherence, suspected malignancy |
| Shared by both ATDs | Cross the placenta → overtreatment causes fetal hypothyroidism and goiter; agranulocytosis risk | Same | — | — |
- ATD agranulocytosis: fever, sore throat or mouth ulcers on PTU or methimazole → stop the drug at once and check a neutrophil count.
- Monitoring targets and drug choices are also summarized in the hyperthyroidism treatment in pregnancy table.
Complications of uncontrolled hyperthyroidism
- Miscarriage, preterm birth, preeclampsia, fetal growth restriction and stillbirth.
- Maternal arrhythmia, heart failure and thyroid storm.
- Fetal/neonatal thyrotoxicosis (transplacental TRAb): fetal tachycardia and goiter; in the newborn, tachycardia, irritability, warm flushed skin and low birth weight. It may appear only after maternal ATDs wash out of the baby, and resolves over weeks to months as maternal antibodies clear.
- Neonatal hypothyroidism with goiter: from maternal ATD overtreatment; transient.
| فخ امتحاني | |
|
In Graves' disease, TRAb must be checked because it crosses the placenta and can cause fetal thyrotoxicosis. Treatment begins with PTU in the first trimester to avoid teratogenicity, and we switch to methimazole/carbimazole in the second trimester due to concern about PTU hepatotoxicity. Maternal free T4 is maintained in the upper normal range with the lowest possible dose to avoid causing fetal hypothyroidism or goiter (and radioactive iodine is absolutely contraindicated). |
تذكر |
| Hypothyroidism vs hyperthyroidism in pregnancy | ||
|---|---|---|
| Feature | Hypothyroidism | Hyperthyroidism |
| Prevalence and top cause | Commoner of the two; iodine deficiency worldwide, Hashimoto thyroiditis in iodine-sufficient regions | <1% of pregnancies; Graves disease ~95% of cases needing treatment |
| Distinguishing clinical clue | Often silent; fatigue, constipation, cold intolerance overlap with pregnancy | Tremor, weight loss or poor weight gain, ophthalmopathy, pretibial myxedema, diffuse goiter |
| Primary drug and adjustment | Levothyroxine; raise dose ~30% as soon as pregnancy is confirmed (needs rise 30–50%) | PTU in 1st trimester → methimazole/carbimazole from 2nd trimester; short-term beta-blocker |
| Biochemical target | TSH below the trimester-specific upper limit (biochemical euthyroidism) | Free T4 at the upper limit of normal (or just above) on the lowest dose |
| Monitoring | TSH every 4 weeks until stable, then at least once per trimester | TSH and free T4 every 2–6 weeks; serial fetal ultrasound if TRAb-positive |
| Key fetal risk | Impaired neurocognitive development | Fetal/neonatal thyrotoxicosis (TRAb) or fetal goiter from overtreatment |
Thyroid Storm
- Thyroid storm is a rare but life-threatening complication of uncontrolled thyrotoxicosis, precipitated by infection, labor, cesarean delivery, or medication noncompliance (also preeclampsia, anemia and surgery). It affects about 1% of pregnant women with hyperthyroidism.
- It presents with hyperthermia, severe tachycardia (out of proportion to the fever), diaphoresis, dehydration, agitation or delirium, vomiting and diarrhea, arrhythmias, heart failure and cardiovascular collapse.
- vs severe preeclampsia: the two can look alike (hypertension, tachycardia, altered mentation); the absence of proteinuria favors thyroid storm, but the conditions can coexist.
- Prognosis: high maternal and fetal mortality if not treated promptly; even in contemporary series, in-hospital mortality of thyroid storm is about 3–11%.
- Diagnosis is clinical — start treatment without waiting for thyroid function results.
Management
- Step 1 – Resuscitate: intensive care, aggressive intravenous fluids, cooling with acetaminophen (not aspirin), oxygen and continuous fetal monitoring.
- Step 2 – Beta-blocker for the adrenergic features — the fastest symptom control: propranolol 60–80 mg orally every 4–6 hours (or an esmolol infusion).
- Step 3 – Immediate PTU: the preferred thionamide, because it blocks synthesis and the peripheral conversion of T4 to T3; loading dose 600–1000 mg, then 200–250 mg every 4 hours.
- Step 4 – Iodine (potassium iodide or Lugol solution) to inhibit hormone release — never before PTU; give it at least 1 hour after the thionamide.
- Step 5 – High-dose corticosteroids: hydrocortisone 300 mg IV, then 100 mg IV every 8 hours (dexamethasone is an alternative).
- Step 6 – Treat the trigger and stabilize before delivery: avoid delivery during the storm unless there is an obstetric indication.
| Thyroid storm drugs: "PB and I + C" | |
|
جملة تذكرية |
Precipitants, features and drug roles are also summarized in the clinical features and treatment of thyroid storm.
| ملاحظة سريرية | |
|
Thyroid storm can clinically resemble severe preeclampsia, but we differentiate them by the absence of proteinuria in thyroid storm, and its emergency treatment relies on PTU because it prevents hormone synthesis and simultaneously blocks the peripheral conversion of T4 to T3. |
ملاحظة |
Key Points for Exams
- Estrogen raises TBG → total T4/T3 about 1.5× normal with a normal free T4; interpret TSH + free T4 with trimester-specific ranges.
- hCG (peak 10–12 weeks) suppresses TSH in the first trimester; low TSH with normal free T4 is usually physiologic.
- The fetal brain depends on maternal T4 in the first half of pregnancy; the fetal thyroid is fully functional only by about 18–20 weeks.
- Iodine, TRAb and antithyroid drugs cross the placenta; maternal T4 crosses in limited amounts; TSH does not cross.
- Known hypothyroidism → increase levothyroxine (~20–30%) as soon as pregnancy is confirmed; check TSH every 4 weeks.
- New overt hypothyroidism in pregnancy → levothyroxine immediately, never expectant management.
- Graves disease causes ~95% of hyperthyroidism needing treatment; ophthalmopathy and pretibial myxedema are specific.
- Hyperemesis + low TSH + negative TRAb, no goiter or eye signs → gestational transient thyrotoxicosis → supportive care, no ATDs.
- PTU in the 1st trimester (methimazole embryopathy, e.g., aplasia cutis); methimazole from the 2nd trimester (PTU hepatotoxicity).
- Target maternal free T4 at the upper limit of normal on the lowest dose; overtreatment → fetal goiter and hypothyroidism.
- Radioactive iodine is contraindicated; ultrasound is the imaging of choice; thyroidectomy, if needed, in the 2nd trimester.
- TRAb persists after maternal thyroidectomy or radioiodine and can still cause fetal/neonatal thyrotoxicosis, which resolves over weeks to months.
- Fever or sore throat on an ATD → stop the drug and check neutrophils (agranulocytosis).
- Thyroid storm: PTU first, iodine ≥1 hour later, plus beta-blocker and steroids; no proteinuria helps separate it from severe preeclampsia.
احصل على التجربة الكاملة
اشترك للوصول لفيديوهات الشرح التفصيلي والبطاقات التعليمية التفاعلية وأسئلة الممارسة مع تتبع التقدم.