Summary
Intrahepatic cholestasis of pregnancy (ICP) is a liver disorder of late pregnancy characterized by pruritus and elevated serum bile acids. Maternal prognosis is good, but fetal risks include preterm birth, meconium-stained amniotic fluid, and stillbirth. Diagnosis is confirmed by bile acids >10 μmol/L, and management involves ursodeoxycholic acid, fetal monitoring, and planned delivery at 36–39 weeks, with resolution postpartum but frequent recurrence. The classic patient is in the late second or third trimester, itching most at night on the palms and soles, with no primary rash. The one thing not to miss is the sudden fetal death that routine fetal testing cannot predict, which is why delivery is planned early.
Overview
Intrahepatic cholestasis of pregnancy (ICP) is the most common pregnancy-associated liver disorder, typically presenting in the second or third trimester. It is characterized by maternal pruritus, particularly nocturnal and most pronounced on the palms and soles, and elevated maternal serum bile acid levels. The condition is of major clinical concern due to its association with adverse perinatal outcomes, while maternal prognosis remains favorable.
- Prevalence: approximately 0.4–10% of pregnancies, varying by geographic and ethnic background.
- Onset: second or (most often) third trimester, when estrogen and progesterone peak.
- Course: resolves after delivery. It is one of the pregnancy-specific liver disorders that disappear once the pregnancy ends, unlike coincidental disease such as viral hepatitis.
- Recurrence: high in subsequent pregnancies (60–90%).
For a one-page recap, see the ICP summary table (features, labs, obstetric risks, management).
Etiology and Risk Factors
The condition results from a combination of three factors:
- Genetic predisposition: the risk is higher with a family history of ICP or with ICP in a previous pregnancy.
- Hormonal influences: elevated estrogen and progesterone slow hepatobiliary flow and reduce bile excretion.
- Drug-induced hepatotoxicity (occasionally): estrogen-containing drugs are a classic trigger of intrahepatic cholestasis.
Key risk factors:
- Advanced maternal age (>35 years)
- Multiple gestation (higher placental hormone load)
- History of ICP in a prior pregnancy
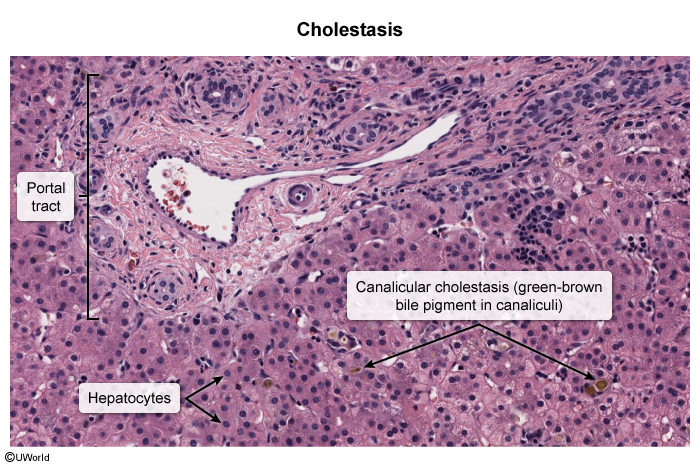
Mechanism in one line: bile acids that the liver fails to excrete spill into the maternal blood and cause itch. They also cross the placenta into the fetal circulation and amniotic fluid, which is where the fetal risk comes from.
Clinical Features and Diagnosis
Clinical features
- Pruritus (hallmark symptom, especially on palms and soles, often worse at night). It is generalized and intense, with no primary rash; the only skin lesions are excoriations from scratching.
- This is the opposite of polymorphic eruption of pregnancy (PUPPP), whose papules start in the abdominal striae and spare the palms and soles. PUPPP responds to topical corticosteroids, which do not help ICP itch.
- Mild focal itch without abnormal labs is benign; see pregnancy-induced skin changes vs ICP.
- Jaundice (in 10–20% of cases)
- Less common: dark urine, pale stools, nausea, fatigue, anorexia, right upper quadrant discomfort.
- Rare: steatorrhea and malabsorption, which can cause fat-soluble vitamin (vitamin K) deficiency with a prolonged PT.
| ملاحظة سريرية | |
|
Any pregnant patient in the 2nd or 3rd trimester presenting with nocturnal pruritus on the palms and soles with no primary skin rash should be considered to have ICP until proven otherwise. Jaundice appears in only 10–20% of cases, so its absence does not exclude the diagnosis. |
ملاحظة |
Diagnosis
Diagnosis is confirmed by serum bile acids >10 μmol/L in a pregnant woman with pruritus after excluding other causes.
- Step 1: Suspect ICP when itch of the palms and soles, with no rash, starts in the second or third trimester.
- Step 2: Order serum total bile acids (most accurate, confirmatory test) together with transaminases. Itch can come before the lab rise, so repeat the tests (often weekly) if the first bile acid level is normal and itching persists.
- Step 3: Exclude other causes before labelling ICP. Check blood pressure, CBC with platelets, creatinine, glucose, PT/INR, urine protein and viral hepatitis serology. RUQ ultrasound is normal in ICP. A normotensive woman with normal platelets and a normal INR fits ICP rather than the other liver disorders of pregnancy.
| Laboratory findings in ICP | ||
|---|---|---|
| Test | Finding in ICP | Exam significance |
| Serum (total) bile acids | >10 μmol/L | Confirmatory test; often rises after the itch starts, so repeat if the first value is normal |
| ALT / AST | Elevated (usually <2× upper limit of normal) | Supportive only; NOT required for the diagnosis |
| Bilirubin | Normal or mildly increased | Only 10–20% become clinically jaundiced |
| GGT / ALP | May be elevated | Less specific; ALP is physiologically high in every pregnancy (placental ALP) |
| PT/INR | Usually normal | Prolonged only with fat malabsorption (vitamin K deficiency) |
| RUQ ultrasound | Normal | Used only to exclude other liver/biliary disease; does not confirm ICP |
| فخ امتحاني | |
|
The confirmatory test is serum bile acids >10 μmol/L. Do not be misled if ALT and AST are completely normal, as transaminase elevation is not required for diagnosis. Additionally, elevated ALP is not specific, as it is physiologically elevated in pregnancy from the placenta. |
تذكر |
Management
Management has three goals: relieve the mother's itch, watch the fetus, and time delivery before the risk of stillbirth climbs.
| Treatment steps in ICP | |
|---|---|
| 1. Pharmacological therapy | |
| Agent | Role |
| Ursodeoxycholic acid (UDCA, ursodiol) — first-line; e.g., 500 mg orally twice daily, titrated within 500–2,000 mg/day to symptoms | Improves pruritus and may lower bile acids; reduces meconium-stained fluid and spontaneous preterm labor, but has not been shown to prevent stillbirth. Oral antihistamines: symptomatic (sedative) relief only, limited efficacy |
| 2. Fetal surveillance | |
| Test | Timing / limitation |
| Antepartum testing, e.g., nonstress test (NST); weekly bile acids and transaminases | Start at the gestational age at which an abnormal result would lead to delivery (or at diagnosis if later). A normal NST does not predict sudden fetal demise |
| 3. Peripartum management | |
| Decision | Details |
| Planned delivery at 36–39 weeks | Earlier within the window with higher bile acids or worsening symptoms. Antenatal corticosteroids if delivery is planned before 37 0/7 weeks and not given before. No preterm delivery on clinical suspicion without laboratory-confirmed bile acids |
| 4. Postpartum | |
| Expectation | Follow-up |
| Pruritus settles within days; labs normalize within weeks after delivery | Persistent abnormal liver tests → look for underlying chronic liver disease; counsel about 60–90% recurrence in future pregnancies |
- First-line: ursodeoxycholic acid. Antihistamines are only an add-on for sleep and comfort.
- Surveillance: antepartum monitoring is recommended, but a reassuring NST does not exclude sudden fetal death. This is why delivery timing, not testing, is the main protection.
- Timing: deliver earlier within the 36–39-week window when bile acids are higher or symptoms are severe.
Complications
While ICP does not significantly affect maternal health, it is associated with important fetal risks. Bile acids cross the placenta and build up in the fetus, and the risk rises with the maternal bile acid level.
- Intrauterine fetal demise: sudden. It occurs in about 0.8% of affected pregnancies overall (vs about 0.3% without ICP), with most cases among women who have the highest bile acid levels.
- Preterm labor and increased risk of preterm birth (spontaneous and iatrogenic)
- Meconium-stained amniotic fluid
- Neonatal respiratory distress syndrome
- Fetal growth restriction: reported in some series, but the association is inconsistent and it is not a classic feature of ICP.
- Maternal: benign course. Rarely, malabsorption causes vitamin K deficiency with a prolonged PT. Itching and labs resolve after delivery.
| Fetal complications of ICP = "PRIM" | |
Bile acids cross the placenta: the mother only itches, the fetus carries the risk — «الأم بتحكّ، والجنين بخطر». |
جملة تذكرية |
| فخ امتحاني | |
|
Maternal prognosis is excellent and symptoms resolve after delivery, but the true risk is to the fetus: sudden IUFD, meconium-stained amniotic fluid, and preterm birth. This is why we initiate UDCA as first-line therapy (not antihistamines alone) and plan for early delivery between 36–39 weeks, since routine fetal surveillance cannot predict sudden fetal demise. |
تذكر |
Key Points for Exams
- Classic stem: second- or third-trimester itch of the palms and soles, worse at night, with no rash → ICP.
- Confirmatory test: serum bile acids >10 μmol/L. Normal ALT/AST do not exclude ICP, and ALP is nonspecific in pregnancy because the placenta makes it.
- First-line treatment: ursodeoxycholic acid. Antihistamines give symptomatic relief only; topical steroids belong to PUPPP, not ICP.
- Prognosis: excellent for the mother. The fetus is at risk of sudden IUFD, meconium-stained fluid, preterm birth and neonatal RDS ("PRIM"), and the risk rises with the bile acid level.
- Delivery: planned at 36–39 weeks, because fetal testing does not predict sudden demise. Give antenatal corticosteroids if delivery is before 37 weeks.
- Course: resolves after delivery but recurs in 60–90% of later pregnancies.
احصل على التجربة الكاملة
اشترك للوصول لفيديوهات الشرح التفصيلي والبطاقات التعليمية التفاعلية وأسئلة الممارسة مع تتبع التقدم.