شرح المدرسين

Summary
Hypertensive disorders of pregnancy (HDP) cause major maternal and fetal complications, including organ failure, placental abruption, growth restriction, and prematurity. They are classified as chronic hypertension, gestational hypertension, preeclampsia–eclampsia, and chronic hypertension with superimposed preeclampsia.The label depends on two things: whether the pressure rose before or after 20 weeks, and whether proteinuria or end-organ dysfunction is present. Hypertension in pregnancy means BP ≥ 140/90 mm Hg on two readings ≥ 4 hours apart, and ≥ 160/110 mm Hg is the severe range.
Any new hypertension after 20 weeks needs a preeclampsia workup (urine protein, platelets, creatinine, transaminases, symptoms) and fetal growth surveillance. Labetalol and nifedipine are first-line, and ACE inhibitors and ARBs are contraindicated. Magnesium sulfate prevents seizures in severe disease. Delivery is the definitive treatment: usually at 37 weeks, and at 34 weeks when severe features are present. The one thing not to miss is severe-range BP: treat it within 30–60 minutes to prevent a maternal stroke.
Overview
- Definition: HDP are a major cause of maternal and perinatal morbidity and mortality worldwide. They are characteristically progressive and unpredictable, and only delivery cures them.
- Frequency: about 1 in 7 US delivery hospitalizations (≈ 15% in 2017–2019, and rising). Gestational hypertension alone complicates 5–10% of pregnancies.
- Mortality: about one-third of women who die during their delivery hospitalization have an HDP diagnosis recorded.
- Normal pregnancy lowers BP: progesterone-driven vasodilation (nitric oxide, prostacyclin) brings BP to its lowest point in the second trimester, and it then returns toward baseline in the third trimester. This can hide preexisting hypertension early in pregnancy and reveal it later.
The disease affects the mother through multi-organ injury and the fetus through placental insufficiency and preterm delivery, which is often iatrogenic to protect the mother:
| Disease characteristics: complications of hypertensive disorders of pregnancy | ||
|---|---|---|
| Category | Maternal | Fetal / neonatal |
| Acute vascular | Stroke (intracerebral hemorrhage — leading cause of maternal death), eclampsia, pulmonary edema / ARDS | Hypoxia, intrauterine fetal demise, stillbirth |
| Placental | Placental abruption, DIC | Fetal growth restriction ± oligohydramnios |
| Renal / hepatic | Acute kidney injury, HELLP syndrome, hepatic hematoma or rupture | — |
| Delivery-related | Cesarean delivery, postpartum hemorrhage, aspiration pneumonia | Preterm birth (often iatrogenic), perinatal death |
| Long-term | Chronic hypertension, cardiovascular disease, diabetes, chronic kidney disease; recurrence in later pregnancies | — |
Classification of Hypertensive Disorders
Current US (ACOG) practice keeps four categories. Each patient is sorted with two questions: did the hypertension start before or after 20 weeks, and is there proteinuria or end-organ dysfunction? The diagnostic criteria of the hypertensive disorders of pregnancy are also summarized on one page.
| Classification Table: Hypertensive disorders of pregnancy: Two questions decide the label: when did the BP rise (before or after 20 weeks), and is there proteinuria or end-organ dysfunction? | |
| Onset before pregnancy or at < 20 weeks | Chronic hypertension |
| Definition | BP ≥ 140/90 mm Hg before conception or first found at < 20 weeks; also diagnosed when hypertension persists > 12 weeks postpartum |
| Cause | Usually essential; may be secondary (renal, vascular, endocrine) |
| New onset at ≥ 20 weeks | Gestational hypertension |
| Definition | New BP ≥ 140/90 mm Hg at ≥ 20 weeks with NO proteinuria and NO end-organ dysfunction |
| Course | Resolves by 12 weeks postpartum (otherwise relabel as chronic hypertension); the final label is confirmed only after delivery because it can progress to preeclampsia at any time |
| New onset at ≥ 20 weeks | Preeclampsia–eclampsia |
| Preeclampsia | New hypertension at ≥ 20 weeks PLUS proteinuria and/or end-organ dysfunction (with or without severe features) |
| Eclampsia | New-onset generalized tonic-clonic seizures in a woman with preeclampsia |
| Preexisting hypertension that worsens | Chronic hypertension with superimposed preeclampsia |
| Definition | Chronic hypertension plus new or worsening proteinuria at ≥ 20 weeks, sudden worsening of previously controlled BP, or new end-organ dysfunction |
- Why 20 weeks matters: hypertension driven by the placenta rarely appears before 20 weeks. Hypertension found earlier is therefore treated as chronic, and it was often undiagnosed before the pregnancy.
- Severity guides management more than the label: preeclampsia is split into with and without severe features (criteria under Diagnosis & Workup). Gestational hypertension with severe-range BP is managed like preeclampsia with severe features.
| Important – فكرة سؤال | |
|
Not all new-onset hypertension after 20 weeks of gestation is preeclampsia. In the absence of proteinuria and end-organ dysfunction, the diagnosis is gestational hypertension. Conversely, if preeclampsia develops prior to 20 weeks, strongly suspect a hydatidiform mole (look for uterus larger than dates, markedly elevated beta-hCG, and a classic "snowstorm" appearance on ultrasound). |
تذكر |
Etiology & Risk Factors
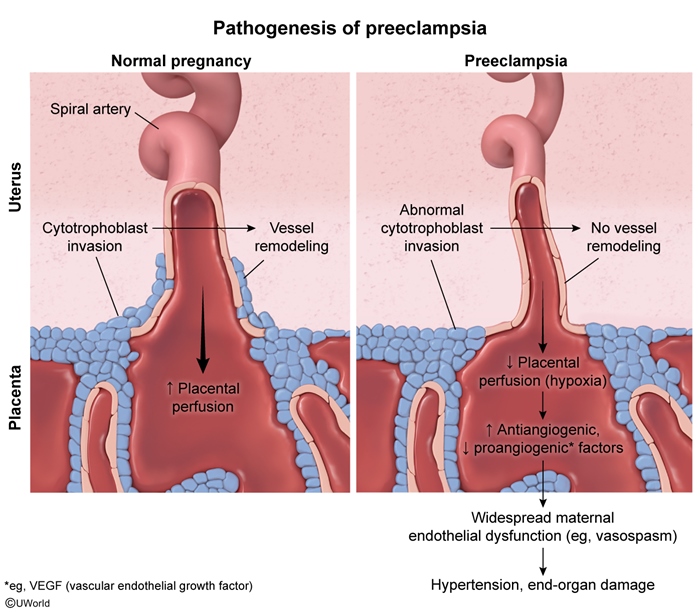
The precise pathogenesis remains unclear, but abnormal placentation with defective remodeling of spiral arteries is central, leading to placental hypoperfusion, endothelial dysfunction, and release of vasoactive and prothrombotic factors.
- Normal placentation: cytotrophoblasts invade the maternal spiral arteries and turn them into wide, low-resistance vessels.
- Defective placentation: shallow invasion leaves the arteries narrow and high-resistance. The ischemic placenta then releases more antiangiogenic factors and fewer proangiogenic factors (VEGF, placental growth factor).
- Maternal result: widespread endothelial dysfunction causes vasospasm (hypertension), leaky capillaries (proteinuria, edema), and hypoperfusion of the liver, kidneys, brain, and platelets.
- Fetal result: reduced uteroplacental flow causes asymmetric growth restriction and oligohydramnios, because blood is redirected away from the fetal kidneys.
- Chronic hypertension: works through the same mechanisms as essential hypertension, but the diseased vessels also impair placentation. This raises the risk of superimposed preeclampsia and abruption.
Most-tested risk factors:
- Nulliparity
- Extremes of maternal age: < 20 or > 35 years
- Chronic hypertension or renal disease, and other chronic vascular disease
- Multiple gestation (larger placental mass)
Diagnosis & Workup
Diagnosis relies on blood pressure ≥ 140/90 mm Hg (a raised systolic or diastolic value alone is enough) on two occasions ≥ 4 hours apart, after 20 weeks' gestation, in previously normotensive women. Severe hypertension is defined as ≥ 160/110 mm Hg. Confirm it within about 15 minutes and start treatment; do not wait 4 hours.
- Step 1: Screen at every prenatal visit. Measure BP each time and record the prepregnancy baseline at the first visit (seated, rested, correct cuff size).
- Step 2: Time the onset. Before 20 weeks → chronic hypertension (get baseline labs). At ≥ 20 weeks → evaluate for preeclampsia.
- Step 3: Ask about end-organ symptoms: headache not relieved by acetaminophen, scotomata or blurred vision, RUQ or epigastric pain, new nausea or vomiting, and dyspnea.
- Step 4: Quantify proteinuria and order labs. If both are normal, the diagnosis is gestational hypertension. If either is abnormal, it is preeclampsia, and you must look for severe features.
- Step 5: Assess the fetus (see below).
Workup includes:
- Urine: the dipstick is only a screen and misses cases. 24-hour urine protein ≥ 300 mg is the gold standard, and a spot protein/creatinine ratio ≥ 0.3 is an accepted alternative. A dipstick of 2+ counts only when quantitative tests are unavailable.
- New hypertension with only trace or 1+ protein on dipstick → do a 24-hour collection before labelling it gestational hypertension.
- Serum: serum creatinine, electrolytes, liver function tests, complete blood count, and LDH. Check for hemolysis with a blood smear; schistocytes plus high LDH point to HELLP syndrome.
- Chronic hypertension: do baseline studies early in pregnancy (CBC, creatinine, transaminases, urine protein/creatinine ratio) so that superimposed preeclampsia can be recognized later. Add an ECG, and echocardiography if the ECG is abnormal, when hypertension is long-standing or poorly controlled.
- Fetal surveillance: ultrasonography (growth, umbilical artery Doppler flow, amniotic fluid), cardiotocography (nonstress test), and biophysical profile. In chronic hypertension, get a first-trimester dating scan and serial growth scans, and start weekly testing from 32 weeks if the patient is on medication.
Management & Timing of Delivery
Management depends on gestational age, disease severity, and maternal-fetal status. Antihypertensives protect the mother from stroke, pulmonary edema, and myocardial ischemia. They do not treat the placental disease and do not prevent growth restriction; only delivery does.
Antihypertensives
- First-line (oral): labetalol and extended-release nifedipine. Methyldopa remains acceptable but acts slowly and causes sedation.
- When to treat: in chronic hypertension, keep BP < 140/90 mm Hg (current US practice after the CHAP trial). In gestational hypertension or preeclampsia, treat severe-range BP (≥ 160/110 mm Hg).
- Severe-range BP: give IV labetalol, IV hydralazine, or immediate-release oral nifedipine within 30–60 minutes of confirmation.
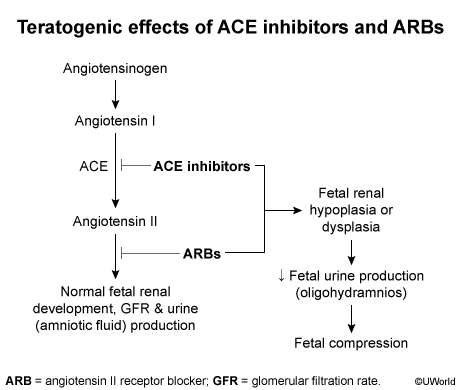
Choose by the patient: avoid labetalol with bradycardia or asthma (hydralazine instead), and avoid oral nifedipine with vomiting. - Contraindicated: ACE inhibitors, ARBs, and direct renin inhibitors, which are fetotoxic (fetal renal hypoplasia → oligohydramnios → Potter sequence). Also avoid spironolactone and nitroprusside (cyanide risk). Atenolol is avoided because it is linked to low birth weight. Switch these drugs before conception or at the first prenatal visit.
- Postpartum: Enalapril is safe in breastfeeding women; methyldopa should be discontinued (within 2 days of delivery) due to risk of postpartum depression.
| Important – فكرة سؤال | |
|
ACE inhibitors and ARBs are fetotoxic across all trimesters, causing fetal renal hypoplasia, oligohydramnios, and subsequent Potter sequence. If a pregnant patient presents on lisinopril or valsartan, discontinue it immediately and switch to labetalol or extended-release nifedipine. However, the rules reverse postpartum: enalapril is safe and compatible with breastfeeding, whereas methyldopa should be tapered and stopped within 2 days postpartum due to an increased risk of postpartum depression. |
تذكر |
| Antihypertensives in pregnancy | ||||
|---|---|---|---|---|
| Labetalol | Nifedipine | Methyldopa | Hydralazine | |
| Class | α1 + β blocker | Dihydropyridine CCB | Central α2 agonist | Direct arteriolar vasodilator |
| Maintenance (oral) | First-line; up to 2,400 mg/day in 2–3 doses | First-line; extended-release up to 120 mg/day | Acceptable; up to 3,000 mg/day in 2–3 doses (slow, weak) | Not used for maintenance |
| Acute severe BP | 10–20 mg IV, then 20–80 mg every 10–30 min (max 300 mg) | Immediate-release 10–20 mg PO, repeat in 20 min if needed (max 180 mg) | Not used (slow onset) | 5–10 mg IV, repeat every 20–40 min (max 20 mg) |
| Avoid / cautions | Asthma, heart failure, bradycardia (HR < 60/min); neonatal bradycardia | Maternal tachycardia; oral route useless if vomiting | Sedation, hepatitis, depression → stop within 2 days postpartum | Reflex tachycardia, maternal hypotension |
| Mnemonic – جملة تذكرية | |
|
"Hypertensive Moms Love Nifedipine"
Never in pregnancy: the RAAS blockers (ACE inhibitors, ARBs, direct renin inhibitors, spironolactone) and nitroprusside. |
جملة تذكرية |
Magnesium sulfate
- Indication: seizure prophylaxis in preeclampsia with severe features, eclampsia, and HELLP syndrome. It is not a blood pressure drug.
- Dose: 4–6 g IV over 20–30 min, then 1–2 g/h, continued for 24 hours after delivery. The IM alternative is 10 g (5 g in each buttock), then 5 g every 4 hours.
- Toxicity: loss of patellar reflexes comes first, then respiratory depression, then cardiac arrest. Stop the infusion and give IV calcium gluconate (magnesium toxicity features and treatment). Magnesium is renally cleared, so watch urine output.
Timing of delivery
Timing of delivery
- ≥ 37 weeks: deliver women with gestational hypertension or preeclampsia without severe features (at diagnosis if it is made later).
- < 37 weeks without severe features: individualized expectant management with close monitoring (BP twice weekly, weekly labs, fetal testing). Corticosteroids may be given for fetal lung maturation if delivery before 34 weeks becomes likely.
- Severe features (or gestational hypertension with severe-range BP): deliver at 34 weeks. Before 34 weeks, stabilize with magnesium and antihypertensives and give corticosteroids if the mother and fetus are stable.
- Chronic hypertension: no medication → 38+0 to 39+6 weeks. Controlled on medication → 37+0 to 39+6 weeks. Difficult to control → 36+0 to 37+6 weeks.
- Immediate delivery after maternal stabilization is indicated for eclampsia, HELLP syndrome, pulmonary edema, placental abruption, DIC, severe refractory hypertension, or non-reassuring fetal status.
- Route: vaginal delivery (usually induction) is preferred. HDP alone is not an indication for cesarean delivery.
| ملاحظة – Note | |
|
Magnesium sulfate is not an antihypertensive; it is solely used for seizure prophylaxis. It is administered in preeclampsia with severe features, eclampsia, and HELLP syndrome, and is not indicated in gestational hypertension or preeclampsia without severe features.
|
ملاحظة |
Prevention and postpartum care
Prevention and postpartum care
- Low-dose aspirin 81 mg daily, started after 12 weeks (between 12 and 28 weeks, ideally before 16) and continued until delivery. Indicated for women with ≥ 1 high-risk factor (prior preeclampsia, chronic hypertension, multifetal gestation, pregestational diabetes, kidney disease, autoimmune disease) or ≥ 2 moderate-risk factors.
- After delivery: BP can rise again around days 3–5 as extravascular fluid returns to the circulation, so recheck it within 3–10 days. Preeclampsia can first appear up to 6 weeks postpartum, typically as a severe headache with high BP, and is treated with antihypertensives and magnesium.
- Follow-up: hypertension persisting beyond 12 weeks postpartum is chronic hypertension and is managed as essential hypertension.
Key Points for Exams – نقاط مهمة للامتحانات
- Hypertension in pregnancy = BP ≥ 140/90 mm Hg on 2 readings ≥ 4 h apart. Severe range ≥ 160/110 mm Hg must be treated within 30–60 min.
- Before 20 weeks = chronic hypertension. New hypertension at ≥ 20 weeks with no proteinuria or organ damage = gestational hypertension, not preeclampsia.
- Preeclampsia before 20 weeks → think hydatidiform mole.
- 24-hour urine protein ≥ 300 mg is the gold standard; a protein/creatinine ratio ≥ 0.3 is equivalent. A weak dipstick does not exclude preeclampsia.
- Severe features: platelets < 100,000/µL, creatinine > 1.1 mg/dL or doubled, transaminases ≥ 2× normal, pulmonary edema, new cerebral or visual symptoms.
- Pathogenesis: failed spiral artery remodeling → placental ischemia → antiangiogenic imbalance → maternal endothelial dysfunction.
- First-line drugs: labetalol and nifedipine (methyldopa acceptable). For acute severe BP: IV labetalol, IV hydralazine, or oral immediate-release nifedipine. Choose hydralazine if the patient is bradycardic or asthmatic.
- ACE inhibitors and ARBs are contraindicated in all trimesters (fetal renal hypoplasia, oligohydramnios, Potter sequence). Switch to a safe drug before conception.
- Antihypertensives prevent maternal stroke. They do not change placental disease or fetal growth.
- Magnesium sulfate = seizure prophylaxis. Its toxicity starts with loss of reflexes; the antidote is calcium gluconate.
- Delivery: 37 weeks for gestational hypertension or preeclampsia without severe features; 34 weeks with severe features; 37–39+6 weeks (38–39+6 if off medication) for chronic hypertension.
- HDP alone is not an indication for cesarean delivery.
- Chronic hypertension raises the risk of superimposed preeclampsia, fetal growth restriction, abruption, and preterm delivery.
- Aspirin 81 mg/day from 12 weeks for women at high risk of preeclampsia.
- Postpartum: enalapril is compatible with breastfeeding; stop methyldopa because of the risk of postpartum depression.
احصل على التجربة الكاملة
اشترك للوصول لفيديوهات الشرح التفصيلي والبطاقات التعليمية التفاعلية وأسئلة الممارسة مع تتبع التقدم.