Summary
UTIs in pregnancy range from asymptomatic bacteriuria to acute cystitis and pyelonephritis, all of which require prompt recognition and treatment to prevent maternal and fetal complications. Routine screening for ASB in early pregnancy, judicious selection of safe antimicrobials, and close follow-up are essential components of management.
Overview
Urinary tract infections (UTIs) are among the most common medical complications of pregnancy and are classified into asymptomatic bacteriuria (ASB), lower urinary tract infection (acute cystitis), and upper urinary tract infection (pyelonephritis).
All bacteriuria in pregnancy warrants treatment, as untreated infections increase the risk of maternal morbidity, pyelonephritis, and adverse pregnancy outcomes such as preterm labor, intrauterine growth restriction, and low birth weight.
Pathophysiology of UTIs in Pregnancy
Pregnancy predisposes women to recurrent bacteriuria and UTIs due to several physiologic changes:
- Progesterone-mediated smooth muscle relaxation → urinary stasis, ureteral dilation, and vesicoureteral reflux.
- Gravid uterus compression → bladder pressure and ureteral obstruction, worse on the right, where the rotated uterus presses on the ureter at the pelvic brim.
- Relative immunosuppression.
These changes → bacterial ascension from the lower to the upper urinary tract.
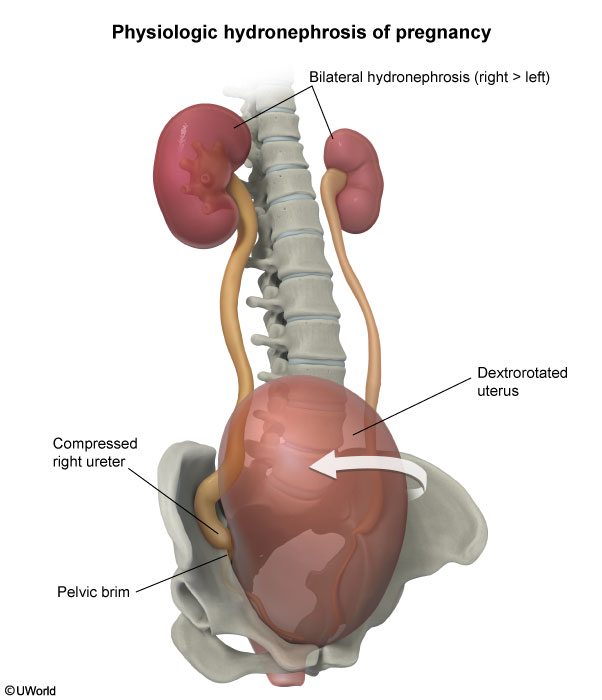
| PRO-G: why pregnancy predisposes to UTI | |
|
جملة تذكرية |
Asymptomatic Bacteriuria (ASB)
- Epidemiology: Occurs in 5–10% of pregnancies; most commonly caused by Escherichia coli (≈80%).
- Risk factors:
- Urinary stasis.
- Glucosuria.
- Alkaline urine in pregnancy.
- Diagnosis: Defined as ≥100,000 CFU/mL on urine culture without urinary symptoms. Universal screening is recommended at the first prenatal visit.
- Complications if untreated:
- Progression to overt UTI: cystitis (30–40%), pyelonephritis (up to 35%).
- Pregnancy-induced hypertension.
- Preterm labor and uterine contractions.
- Fetal growth restriction: intrauterine growth restriction and low birth weight.
| Important - Question Idea | |
|
Exam trap: Unlike non-pregnant women, any pregnant woman with a urine culture ≥100,000 CFU/mL at the first prenatal visit must be treated even if she has no symptoms, because untreated ASB can progress to pyelonephritis in up to 35% of cases and cause preterm labor. |
تذكر |
Treatment: a 5–7-day oral course, or fosfomycin as a single dose.
| Outpatient oral antimicrobials in pregnancy | |
|---|---|
| Category | Agents and restrictions |
| First-line 5–7 day regimens | Cephalexin, oral cephalosporins, amoxicillin/clavulanate |
| Single-dose option | Fosfomycin |
| Use with caution / timing restrictions | Nitrofurantoin: avoid near term; in the 1st trimester, only if no suitable alternative TMP-SMX: avoid in the 1st trimester and after 32 weeks |
| Avoided in outpatient therapy | Fluoroquinolones, aminoglycosides |
See the antibiotics recommended and contraindicated in pregnancy for the full list. Sources differ on the exact late limit for TMP-SMX.
| TERM-1-32: oral antibiotic timing traps | |
|
جملة تذكرية |
- Follow-up: A follow-up urine culture is recommended 1 week post-therapy.
| Note – ملاحظة | |
|
Exam trap: Pay attention to timing: nitrofurantoin is contraindicated near term, and TMP-SMX is contraindicated in the 1st trimester and after 32 weeks. Always request a follow-up urine culture one week after completion of therapy to ensure eradication. |
ملاحظة |
Acute Cystitis
- Epidemiology: Occurs in ~1% of pregnancies.
- Clinical features:
- Dysuria, urinary frequency, urgency.
- Suprapubic pain without systemic symptoms.
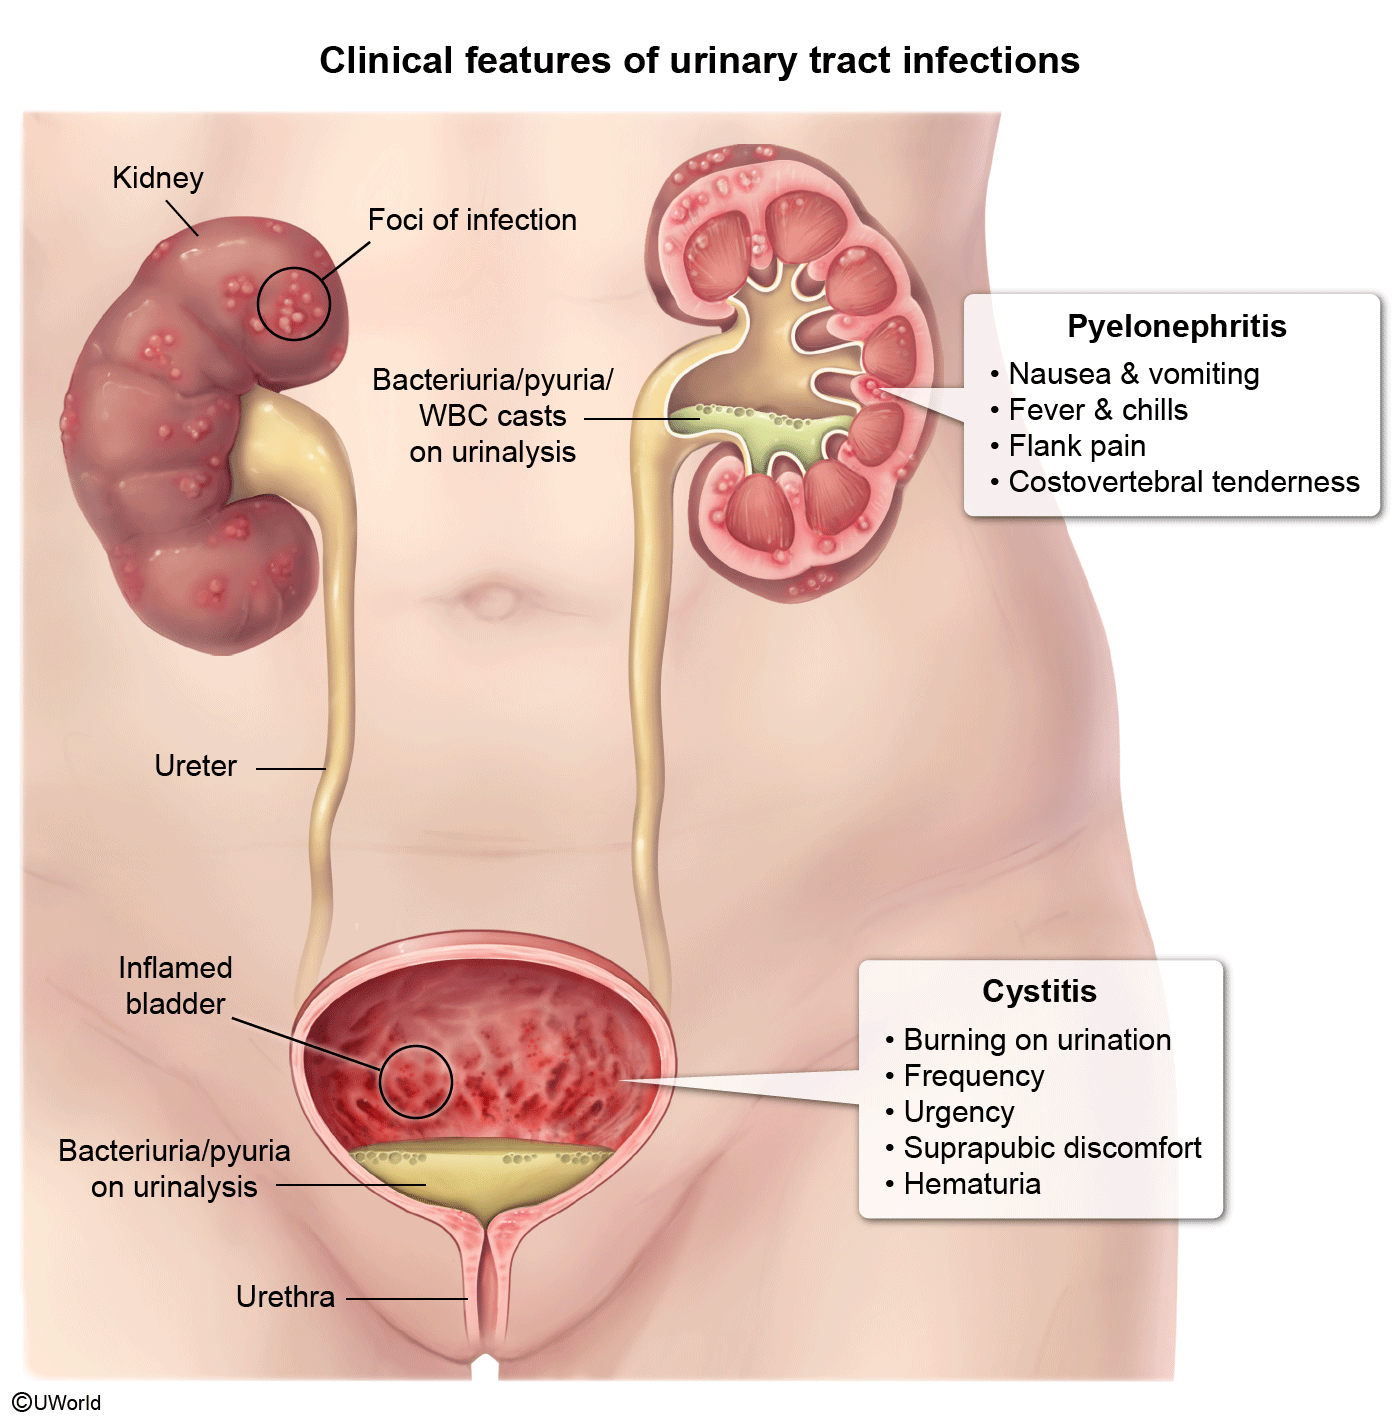
- Diagnosis: Confirmed by urine culture ≥100,000 CFU/mL in a symptomatic patient.
- Treatment:
- Same antibiotic regimens as for ASB (see the table in the ASB section), generally for 5–7 days. The management of cystitis and ASB in pregnancy shows both conditions side by side.
- Repeat urine culture may be considered after completion of therapy, especially in recurrent cases.
| Ampicillin: avoided alone, used in combination | |
|
تذكر |
| Note – ملاحظة | |
|
Clinical Note: acute cystitis presents with lower urinary tract symptoms (dysuria, frequency, urgency, suprapubic pain) without systemic fever. Empiric oral treatment is given for 5–7 days; however, avoid ampicillin or amoxicillin monotherapy due to high Escherichia coli resistance. |
ملاحظة |
Acute Pyelonephritis
- Epidemiology: Affects 1–2% of pregnancies, more often primigravidas and more common on the right side.
- Risk factors:
- Untreated ASB.
- Progression from cystitis.
- Ureteral obstruction, or instrumentation during labor.
- Clinical features:
- Fever ≥38°C.
- Flank pain.
- Costovertebral angle tenderness.
- Malaise, chills.
- Nausea.
- Dehydration.
- Systemic toxicity.
- Up to 20% of cases are associated with uterine contractions and preterm labor.
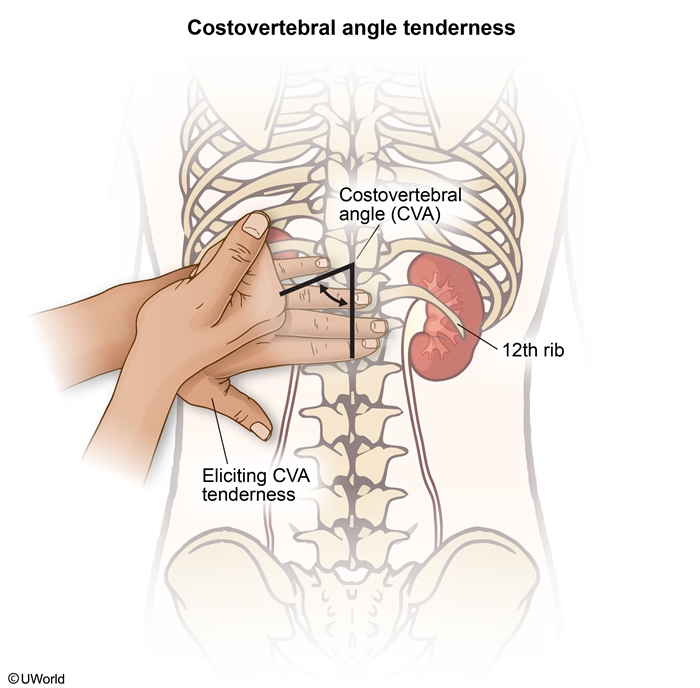
- Diagnosis: Clinical suspicion supported by positive urine culture and systemic symptoms. See the risk factors, pathogens and complications of pyelonephritis in pregnancy and the genitourinary causes of acute abdominal pain.
Inpatient management:
- Step 1: All cases require hospitalization.
- Step 2: Aggressive IV fluids, with monitoring of renal function and electrolytes. Watch the respiratory status as well: pyelonephritis in pregnancy can cause pulmonary edema and ARDS.
- Step 3: Continuous fetal assessment.
- Step 4: Empiric parenteral antibiotics (e.g., cephalosporins such as ceftriaxone, aminoglycosides with caution, or ampicillin plus gentamicin), tailored to culture results. See UTI treatment during pregnancy for the options by severity.
- Step 5: IV antibiotics are continued until the patient is afebrile and clinically stable, followed by oral therapy to complete a 14-day course. Use a culture-guided agent such as cephalexin. Nitrofurantoin and fosfomycin do not treat pyelonephritis, because kidney tissue levels are too low.
- Step 6: Suppressive therapy for the remainder of pregnancy may be considered in recurrent cases.
| Note – ملاحظة | |
|
Clinical note: Pyelonephritis in pregnancy is more common in primigravidas and on the right side, and all cases require hospitalization: aggressive IV fluids and continuous fetal assessment and IV antibiotics until the patient is afebrile and clinically stable, followed by oral therapy to complete a 14-day course. In recurrent cases, add suppressive therapy for the remainder of pregnancy. |
ملاحظة |
| Comparison of UTIs in pregnancy | |||
|---|---|---|---|
| Attribute | Asymptomatic bacteriuria | Acute cystitis | Pyelonephritis |
| Epidemiology | 5–10% of pregnancies | ~1% of pregnancies | 1–2% of pregnancies; primigravidas, right side |
| Clinical presentation | No urinary symptoms | Dysuria, frequency, urgency, suprapubic pain; no systemic symptoms | Fever ≥38°C, flank pain, CVA tenderness, systemic toxicity |
| Diagnostic criteria | ≥100,000 CFU/mL on culture, no symptoms | ≥100,000 CFU/mL in a symptomatic patient | Clinical suspicion + positive culture + systemic symptoms |
| Primary antibiotic strategy & duration | Oral, 5–7 days, or single-dose fosfomycin | Oral, generally 5–7 days; never ampicillin or amoxicillin alone | Hospital; IV until afebrile and stable, then oral to complete 14 days |
| Follow-up & suppression | Urine culture 1 week after therapy | Repeat culture may be considered, especially if recurrent | Suppression for the rest of pregnancy may be considered in recurrent cases |
Key Points for Exams
- All bacteriuria in pregnancy is treated, even without symptoms.
- Screening: urine culture at the first prenatal visit; ASB = ≥100,000 CFU/mL without symptoms.
- Most common organism: Escherichia coli (≈80%).
- Untreated ASB: cystitis 30–40%, pyelonephritis up to 35%.
- First-line oral therapy: cephalexin, oral cephalosporins, or amoxicillin/clavulanate for 5–7 days; fosfomycin is the single-dose option.
- Nitrofurantoin: avoid near term; 1st trimester only if no suitable alternative.
- TMP-SMX: avoid in the 1st trimester and after 32 weeks.
- Ampicillin or amoxicillin alone: not for empiric therapy (high E. coli resistance).
- Aminoglycosides: avoided in routine outpatient UTIs; used with caution, with ampicillin, in hospitalized pyelonephritis.
- Fluoroquinolones: avoided.
- Test of cure: follow-up urine culture 1 week after therapy.
- Cystitis vs pyelonephritis: lower urinary symptoms without systemic features vs fever, flank pain and costovertebral angle tenderness.
- Pyelonephritis: more common in primigravidas and on the right; up to 20% have contractions and preterm labor.
- Pyelonephritis treatment: always hospitalize; IV antibiotics until afebrile and stable, then oral to complete 14 days. Never nitrofurantoin or fosfomycin.
- Recurrent cases: consider suppressive therapy for the remainder of pregnancy.
احصل على التجربة الكاملة
اشترك للوصول لفيديوهات الشرح التفصيلي والبطاقات التعليمية التفاعلية وأسئلة الممارسة مع تتبع التقدم.